Further learning
Identifying triggers of delirium
Check for urgent illness, look for possible causes, and repeat the assessment if the person is not improving as expected.
About this module
When someone has delirium, the team needs to find out what may be causing it. Look for acute illness, changes in normal body function, medicine effects, pain and other unmet needs, and problems with the care environment. Several factors may contribute. Begin urgent treatment and supportive care while this assessment continues.
Before you start: With JavaScript and browser storage available, quiz answers and your place are saved in this tab for the current browser session. Names and completion certificates are not saved. Print or save your completion certificate before leaving.
Learning outcomes8 outcomes
By the end, you should be able to
- Explain how background vulnerability and acute triggers can combine to produce delirium.
- Recognise clinical instability that requires an immediate emergency response.
- Assess the person for several possible causes and contributing factors.
- Gather useful evidence from the person, family or carers, staff, records, observation, and examination.
- Describe why investigations should be guided by the history and clinical findings.
- Avoid common errors, including stopping at the first plausible cause or equating bacteriuria with symptomatic urinary tract infection.
- Record possible contributors, actions, responsibility, and response clearly.
- Reassess when delirium persists, fluctuates, or worsens.
First: check for clinical instability and use the local emergency response when needed.
- Acute illnessCheck observations and signs of deterioration
- Neurological problemsInjury and neurological findings
- MedicinesCheck changes, doses and combined effects
- Physical needsPain, bladder, bowel and intake
- Function and settingSenses, mobility, sleep and environment
Then: act, record and review the response. Repeat the assessment if delirium persists, fluctuates, worsens, or does not respond as expected.
1. Understand risk factors and causes
A delirium assessment has two linked questions:
- Does this person have delirium?
- What may have caused, triggered, or prolonged it?
A tool such as the 4AT helps detect possible delirium. It does not identify the cause. The final diagnosis and cause assessment remain clinical.
Some people have greater background vulnerability because of dementia, frailty, severe illness, multimorbidity, or sensory impairment. They may develop delirium after a relatively modest acute disturbance. A person with less vulnerability may require a more severe disturbance. Age, dementia, or frailty can therefore affect risk, but none is an adequate explanation for a new acute change.
How vulnerability and acute triggers combine
A person with greater background vulnerability
A person with less vulnerability
Possible acute contributors include infection or another acute illness, hypoxia, circulatory or metabolic disturbance, medication effects, a recent operation or procedure, pain, dehydration, urinary retention, constipation, immobility, sleep disruption, and an unfamiliar care environment. Several may coexist (Ormseth et al. 2023).
In practice, causation is not always certain. Record a finding as a possible contributor unless the evidence supports a more definite conclusion. Treat a likely cause while continuing to look for other contributing problems.

2. Check for clinical instability first
Delirium may be the first sign of serious acute illness. Before working through a cause list, decide whether the person is clinically unstable or deteriorating.
Use the emergency assessment and escalation process for your setting if there are concerns such as:
- a problem with airway, breathing, or circulation;
- new marked hypoxaemia, hypotension, or other abnormal physiological observations;
- markedly reduced consciousness or rapid deterioration;
- suspected sepsis;
- a new focal neurological deficit, seizure, or recent head injury; or
- concern about poisoning, intoxication, or withdrawal.
Complete the immediate bedside assessment and physiological observations required by the local deterioration pathway. Begin urgent treatment and call for the appropriate clinical help. Cause-finding, collateral history, and delirium assessment can continue alongside this care when it is safe to do so.
3. Look for possible causes
Once urgent treatment has begun, check the following possible causes and contributing factors. Adapt the assessment to the person and setting.
- Acute illness and physiology: consider infection, hypoxia, cardiorespiratory illness, dehydration, bleeding, and disturbances of glucose, electrolytes, renal function, or other physiology.
- Neurological illness and injury: consider stroke, seizure and the period after a seizure, intracranial disease, and head injury when the history or findings suggest them.
- Medicines and substances: check recent starts, dose changes, omitted or stopped medicines, adverse effects, interactions, and the cumulative burden of medicines with anticholinergic effects (which can impair memory, attention, bladder and bowel function) or sedative effects (which can reduce alertness). Include prescribed, non-prescribed, and as-required medicines, and what was actually administered (Reisinger et al. 2023; Ieong et al. 2024).
- Pain and physical needs: look for pain, urinary retention, constipation, thirst, poor intake, immobility, pressure-related discomfort, and another source of unexpressed distress.
- Function, senses, sleep, and environment: check hearing and vision, mobility, sleep interruption, changes of room or care setting, unfamiliar routines, and barriers to communication.
The timing, examination and other findings help you decide which of these possibilities are most likely and need attention first.

Mnemonics such as PINCH ME can be useful memory prompts. They are not complete cause lists, diagnostic tools, or substitutes for clinical assessment.
4. Find evidence for possible contributors
Talk with the person
Ask about new symptoms and about pain, breathlessness, thirst, nausea, bowel and bladder problems, sleep, fear, and recent events. Use short questions, hearing or language support, and enough time for a response. A person with severe inattention or drowsiness may not be able to give a reliable history, but should still be included as far as possible.
Establish baseline and recent course
Ask family, carers, familiar staff, or another person who knows the patient about usual cognition and function, the onset and fluctuation of the change, recent illness, falls, procedures, intake, bowel and bladder function, and changes in care setting. Check previous records when collateral information is not immediately available.
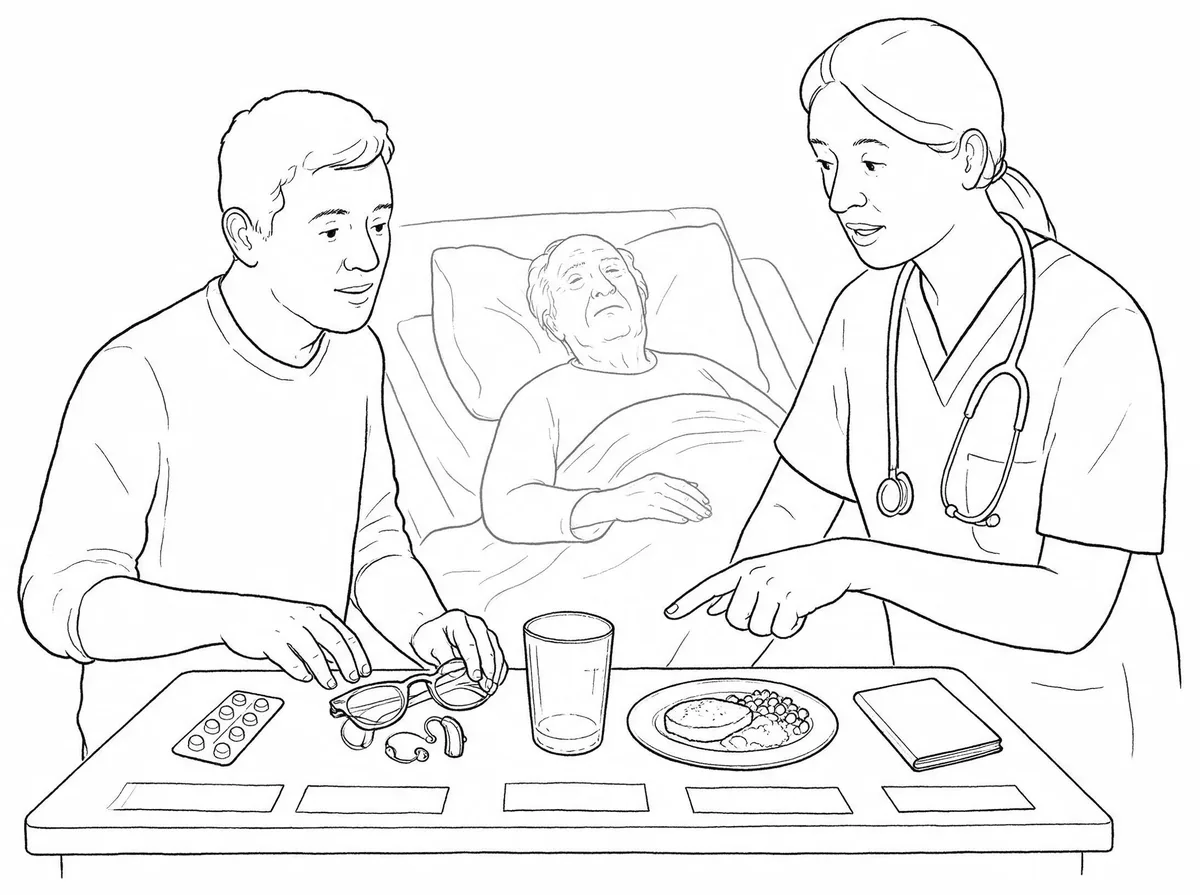
Review records and medicines
Look at observation charts, fluid and food intake, bowel and bladder records, recent procedures, falls, and the clinical course. Reconcile the medicine list with the administration record. Ask about recent prescriptions, dose changes, as-required doses, missed regular medicines, non-prescription products, and substance use. If a medicine may be contributing, ask the prescriber and pharmacist to review the balance of benefit and harm. Do not stop essential medicines outside your role or without considering withdrawal and the condition being treated (Weidmann et al. 2025).
Examine and observe
Use a focused but sufficiently broad physical and neurological examination, guided by the presentation. Observe breathing, movement, facial expression, guarding, swallowing, skin, and the person’s response to care. Consider hidden pain, retention, or constipation in a person who is quiet, drowsy, or unable to describe symptoms.
Select investigations to answer clinical questions
Investigations should follow the history, collateral information, observations, and examination. The tests needed will vary with the findings and care setting. Use current local guidance and choose bedside tests, blood tests, microbiology, imaging, or specialist assessment when each has a clinical indication. Review the results in context rather than treating an isolated abnormality as the explanation.
Four sources of evidence, then chosen tests
Then use what you found:
Current UKHSA and NHS England primary care guidance says not to perform urine dipsticks in adults over 65 because they are unreliable for ruling urinary tract infection in or out. Follow the urinary tract infection guidance for the person’s setting. Asymptomatic bacteriuria, meaning bacteria in the urine without symptoms or signs attributable to urinary tract infection, is common in older people. Bacteriuria or a positive culture alone does not establish symptomatic urinary tract infection or prove that it caused the delirium. If fever, unstable blood pressure or circulation, or concern about sepsis is present, assess urgently, look for all possible infection sources, and follow local infection and sepsis guidance. Do not infer a urinary source from bacteriuria alone (Stall et al. 2024).

Observation activity · Not part of the scored quiz
Watch closely: the meal tray
Observation task: Watch the whole 15-second clip. What can the team conclude from this observation?
Simulated teaching scene.
- Treat the observation as evidence of depression and record this as the cause of poor intake.
- Record that a meal was offered; no further action is needed unless the person asks for help.
- Check alertness and whether eating and drinking are safe; then support intake and assess possible contributors.
- Remove the tray and ask the next shift to review intake before deciding whether to assess further.
Reveal the answer and commentary
Best answer: C.
The clip shows no food being eaten during these 15 seconds. It does not establish the person’s overall intake or why they did not eat. Check alertness, seating position, dentures and oral comfort, and whether eating and drinking are safe. Provide any prescribed assistance, support intake appropriately, and review overall intake and several possible contributors rather than assigning one cause from appearance alone.
Read the video transcript
His spoon hovers over the soup, motionless. A healthcare assistant asks, “Will you try a wee drop of soup for me, John?” He lowers the spoon. Nothing has been eaten.
5. Avoid common assessment errors
Stopping after the first finding. Pneumonia, a recent operation, or a medication change may be relevant, but another contributor can be present at the same time. Look for other contributors and review the response to treatment.
Treating an association as proof. A laboratory abnormality or positive culture may be incidental. Ask whether it fits the symptoms, examination, timing, and wider clinical picture.
Assuming a quiet person is comfortable or well. Hypoactive delirium can accompany severe illness, pain, thirst, urinary retention, constipation, or fear. Look, ask, and examine.
Using a delirium tool to identify the cause. The 4AT detects possible delirium; it does not distinguish infection, medicine effects, pain, or other triggers.
Ordering the same tests for everyone. Indiscriminate testing can produce incidental findings and does not replace a clinical assessment. Tests should answer a question raised by the history or findings.
Writing “delirium due to infection” too early. State what is known, what is suspected, what has been done, and what still needs review. Update the assessment as evidence changes.
Common errors and what to do instead
Example case: assessment and care
6. Mr Lewis: several contributing problems
This is an example case drawn from clinical experience. It does not describe one real patient.
Mr Lewis, aged 82, is admitted with pneumonia. His daughter says that he usually manages his own personal care, reads the newspaper, and walks with a stick. Within a day of admission he develops acute, fluctuating inattention and drowsiness. A 4AT suggests likely delirium, which is confirmed by clinical assessment. Treatment for pneumonia begins.
On day three, his temperature and oxygen requirement are improving, but he is sleepier and drinks very little. He grimaces when moved, has not opened his bowels for four days, and repeatedly reaches towards his lower abdomen. The medicine administration record shows that he has received several doses of a newly prescribed opioid for rib pain.

Look again
The team first checks that Mr Lewis is clinically stable. Collateral information and the records confirm that the drowsiness is new. Examination suggests suprapubic fullness, and assessment under the local pathway supports urinary retention. The team now records several possible contributors:
- pneumonia, which is improving but may still be contributing;
- rib pain;
- poor fluid and food intake;
- constipation;
- urinary retention; and
- possible adverse effects from the new opioid, while recognising that undertreated pain may also worsen delirium.
These problems are addressed in parallel. Pneumonia treatment continues. The clinical team manages urinary retention and constipation, supports hydration and nutrition, and reviews the analgesic plan with the prescriber and pharmacist. Nursing and therapy staff support orientation, comfort, sleep, and safe mobility. Over the next two days, Mr Lewis becomes more alert and starts to mobilise, although his attention still fluctuates. Improvement after several simultaneous interventions does not establish which treatment helped most.
7. Act, record, and look again
Do not wait for certainty before addressing a serious or readily remediable problem. Prioritise threats to life and safety, then manage likely contributors in parallel within the person’s overall goals of care. Continue orientation, communication, hydration, nutrition, pain assessment, mobility, sensory support, and sleep protection while cause-specific treatment proceeds.
Act, record and look again
If delirium persists, worsens or follows an unexpected course, repeat the history, examination and medicine review, look for new problems and reconsider the diagnosis.
Keep a current contributor list so staff across professions and shifts can see the reasoning:
| Possible contributor | Evidence for and against | Action | Responsible person or team | Review time and status |
|---|---|---|---|---|
| What might be contributing? | What in the history, timing, examination, or results supports or weakens it? | What has been done or is planned? | Who will act and follow up? | When will it be checked, and is it improving, unchanged, or worse? |
Document more than “confused” or “delirium due to infection”. Record:
- the person’s usual cognitive and functional baseline and the source of that information;
- onset, fluctuation, and exact changes observed;
- clinical stability and any urgent escalation;
- possible contributors and the evidence for them;
- actions, named responsibility, response, and outstanding results; and
- the next review and what should trigger earlier escalation.
Example handover
“Mr Lewis has confirmed delirium with a fluctuating course. His pneumonia is improving. Pain, poor intake, constipation, urinary retention, and the effects of a new opioid are also possible contributors. Retention and constipation have been treated. The nurse responsible for his care will reassess alertness, intake, pain, bowel and bladder function, mobility, and observations this evening. The medical team will review the opioid today. Escalate any deterioration through the local pathway.”
Delirium may take time to improve after treatment starts. If it persists, worsens, or follows an unexpected course, repeat the history, examination and medication review, and look again for possible causes. Check whether treatments were delivered and effective, whether a new problem has arisen, and whether the diagnosis needs reconsideration. Seek senior or specialist advice when the clinical picture remains unclear.

Further information to use and share
For practitioners: use NICE guidance on delirium, the Australian Delirium Clinical Care Standard, and the delirium or acute deterioration pathway for your own service. For urinary findings, use the current UKHSA and NHS England urinary tract infection diagnostic guidance.
For delirium assessment: the official 4AT website provides the assessment, user guidance, translations, FAQs, and case examples.
For patients, families, and carers: Delirium Support provides plain-language information to use alongside local advice and contact details.
These links open in a new tab so that your place in the module is preserved.
Before the questions
These questions review the main points. A score of 8 out of 10 lets you create a personal completion certificate. You can review the explanations and try again. The video observation activity above does not count towards this score.
Knowledge check
Choose one answer for each question. With JavaScript and browser storage available, answers and your place are saved in this tab for the current browser session. Scores and completion-record names remain in the current page. These details are not sent to Delirium Academy. Browser session restoration may bring back saved answers; use Clear all answers to remove them.
Privacy note: the site host and security services may retain standard access logs, as on ordinary websites, but the module does not put quiz answers or the completion-record name into those requests.
0 of 10 questions answered.
Your result
Create your completion certificate
Add your name to create a personal completion certificate. Your name remains only in this browser page and is not sent to or stored by Delirium Academy.
Certificate of completion
Learner name
This records completion of the Delirium Academy online module Identifying triggers of delirium.
- Knowledge-check result
- 0/10
- Completion date
- Module
- Further learning
- Estimated duration
- 20 minutes
- Provider
- Delirium Academy
- Source check
- 8 August 2026
This record confirms completion of this module and shows the knowledge-check result achieved.
Clinical author: Professor Alasdair MacLullich, Professor of Geriatric Medicine, University of Edinburgh; Consultant Physician; co-developer of the 4AT. Affiliation is given for identification only. Delirium Academy is an independent personal project.
Continue learning
- Review Delirium in 30 if you want to revisit recognition, the 4AT, prevention, initial care, and communication.
- Use the delirium and acute deterioration guidance for your own service and professional role.
- Share Delirium Support with patients, families, and carers alongside local advice and contact details.
- Visit the Links page for further resources and national guidelines.
Research references
Selected peer-reviewed research published within the last five years. Each link opens the verified PubMed record.
- Ormseth, C.H., LaHue, S.C., Oldham, M.A., et al. (2023) ‘Predisposing and precipitating factors associated with delirium: a systematic review’, JAMA Network Open, 6(1), e2249950. Available at: https://pubmed.ncbi.nlm.nih.gov/36607634/.
- Reisinger, M., Reininghaus, E.Z., De Biasi, J., et al. (2023) ‘Delirium-associated medication in people at risk: a systematic update review, meta-analyses, and GRADE-profiles’, Acta Psychiatrica Scandinavica, 147(1), pp. 16-42. Available at: https://pubmed.ncbi.nlm.nih.gov/36168988/.
- Stall, N.M., Kandel, C., Reppas-Rindlisbacher, C., et al. (2024) ‘Antibiotics for delirium in older adults with pyuria or bacteriuria: a systematic review’, Journal of the American Geriatrics Society, 72(8), pp. 2566-2578. Available at: https://pubmed.ncbi.nlm.nih.gov/38895992/.
- Ieong, C., Chen, T., Chen, S., et al. (2024) ‘Differences of anticholinergic drug burden between older hospitalized patients with and without delirium: a systematic review and meta-analysis based on prospective cohort studies’, BMC Geriatrics, 24(1), 599. Available at: https://pubmed.ncbi.nlm.nih.gov/38997670/.
- Weidmann, A.E., Matthíasdóttir, R., Proppé, G.B., et al. (2025) ‘Medication causes and treatment of delirium in patients with and without dementia’, Brain and Behavior, 15(7), e70706. Available at: https://pubmed.ncbi.nlm.nih.gov/40686036/.
Clinical guidance and practical resources (5)
References checked on 8 August 2026. Language edited on 27 September 2026.