Case 23 of 40
Eating, drinking and movement need continuing monitoring during delirium
Example case for staff education
Select an illustration to enlarge it.

Read the case transcript
Page 1
Panel 1: Day 1
Fever, dysuria and flank pain accompany new confusion.
Martin: Yesterday he could follow everything we discussed.
Panel 2: Day 1
Assessment supports pyelonephritis with delirium.
Ward doctor Amira: We will treat the infection and check other possible causes.
Panel 3: Day 3
The fever improves; he forgets how to begin drinking.
Peter: What am I meant to do with this?
Panel 4: Day 3
Access to a drink is not enough.
Nurse Tom: I will stay and help you.
Panel 5: Day 4
Repeated observations show inadequate intake.
Dietitian Beth: We need a plan based on what he actually eats.
Panel 6: Day 4
He has spent much of the day immobile.
Nurse Tom: Let us move gently and check your skin.
Panel 7: Day 5
New swallowing difficulty prompts assessment.
Nurse Tom: We will pause and get advice before continuing.
Panel 8: Day 6
A new fever and hypoxia suggest another acute problem.
Ward doctor Amira: Repeat the examination and investigate this change.
Panel 9: Day 6
Aspiration pneumonia is diagnosed and treated.
Martin: He has a second illness while still confused.
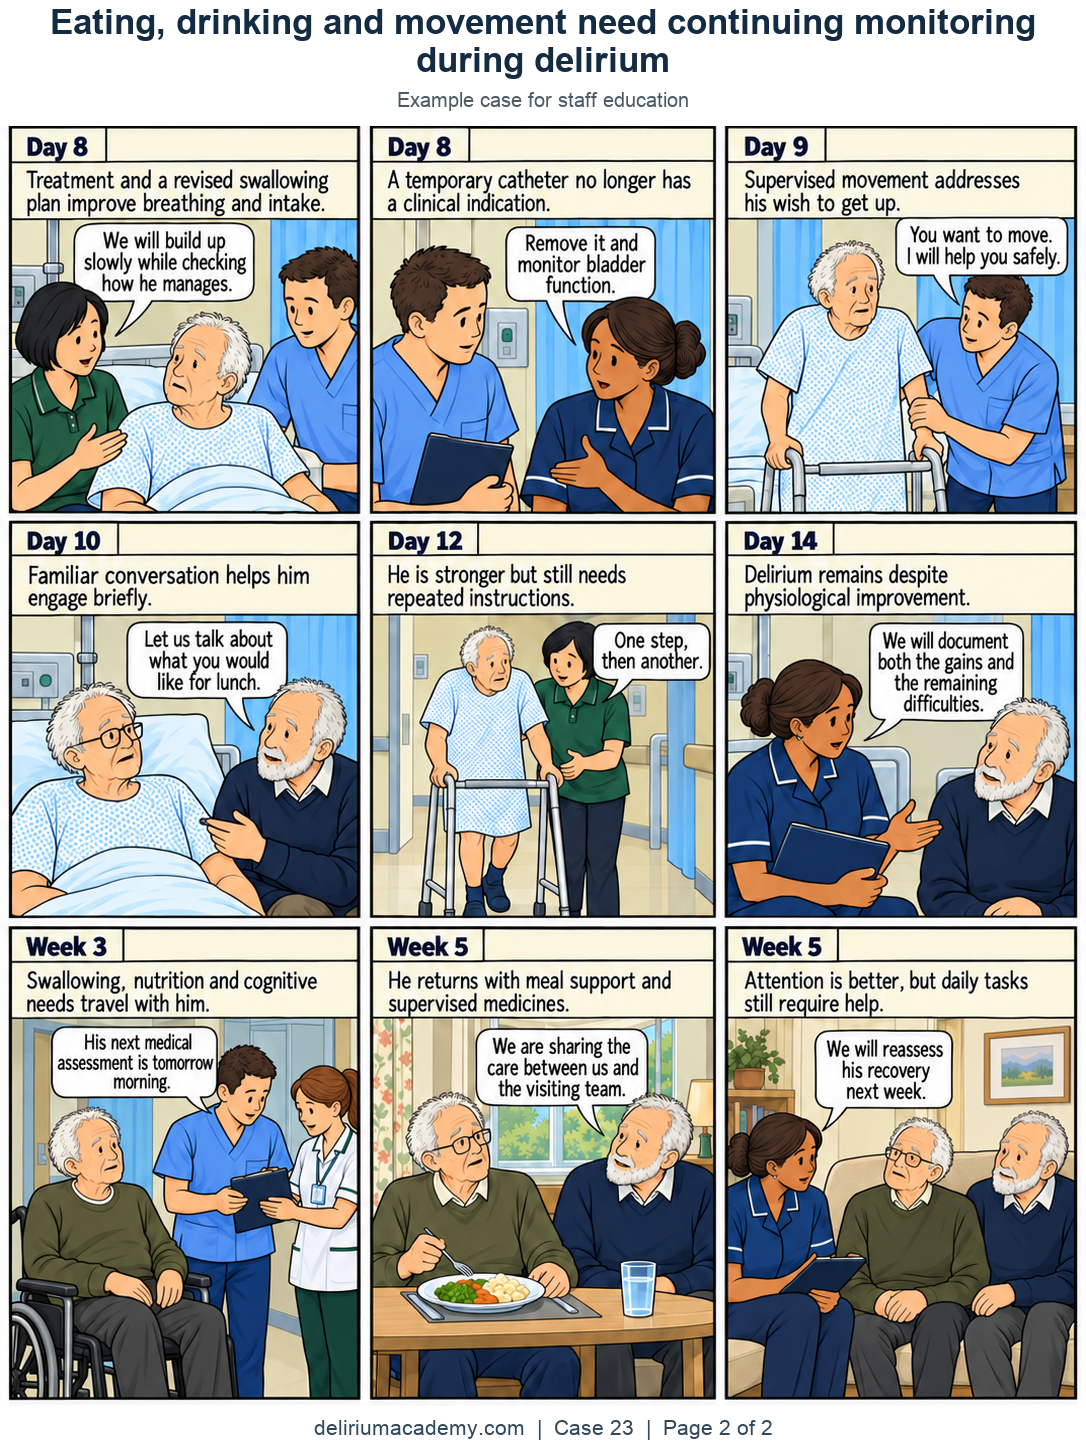
Page 2
Panel 10: Day 8
Treatment and a revised swallowing plan improve breathing and intake.
Physiotherapist Lin: We will build up slowly while checking how he manages.
Panel 11: Day 8
A temporary catheter no longer has a clinical indication.
Ward doctor Amira: Remove it and monitor bladder function.
Panel 12: Day 9
Supervised movement addresses his wish to get up.
Nurse Tom: You want to move. I will help you safely.
Panel 13: Day 10
Familiar conversation helps him engage briefly.
Martin: Let us talk about what you would like for lunch.
Panel 14: Day 12
He is stronger but still needs repeated instructions.
Physiotherapist Lin: One step, then another.
Panel 15: Day 14
Delirium remains despite physiological improvement.
Ward doctor Amira: We will document both the gains and the remaining difficulties.
Panel 16: Week 3
Swallowing, nutrition and cognitive needs travel with him.
Nurse Tom: His next medical assessment is tomorrow morning.
Panel 17: Week 5
He returns with meal support and supervised medicines.
Martin: We are sharing the care between us and the visiting team.
Panel 18: Week 5
Attention is better, but daily tasks still require help.
Ward doctor Amira: We will reassess his recovery next week.
Sources
- [P43] Dharmarajan K, Swami S, Gou RY, Jones RN, Inouye SK. Pathway from Delirium to Death: Potential In-Hospital Mediators of Excess Mortality. Journal of the American Geriatrics Society. 2017;65:1026–1033.
- [S04] Nair, A., Arfan, S., Holder, S.S., Bacchus, K.I. and Stear, T.J. (2023) ‘Persistent Postoperative Delirium Following Laparoscopic Cholecystectomy’, Cureus, 15(6), e40523.
- [G01] National Institute for Health and Care Excellence. Delirium: prevention, diagnosis and management in hospital and long-term care. CG103.
Commentary
Peter’s original infection is treated promptly, but he then needs help to start and continue eating and drinking. He spends long periods without moving and needs repeated explanations of his care. These needs require attention even when blood tests for inflammation improve. New medical complications may also develop.
Dharmarajan and colleagues found that several harmful hospital exposures occurred more often in patients who developed delirium [P43]. Their analysis of deaths was observational. It does not prove that one exposure caused a particular death. The study helps explain why staff should check everyday care needs; it does not provide an individual risk estimate for Peter.
A new cough, fever and low oxygen level prompt assessment for a new illness. Staff reassess swallowing and change the plan. They keep the catheter only while there is a clinical need and adapt help with movement to what Peter can manage. These decisions need repeated review during his illness.
Peter partly recovers but continues to need support. Walking and eating improve before he can reliably organise daily tasks. His discharge plan specifies the help needed and an early reassessment. Observe him during meals and transfers, pass on those findings and identify new changes that need urgent medical review. Continue delirium care after the infection improves [G01].